Acute Bronchitis: Symptoms and Assessment
Understand common cough and sputum symptoms, when clinical assessment matters, and the limited scope of antibiotic guidance.
Publication & corrections: infostoa · Editorial standards
Individual author and specialist reviewer information is not provided for this article.
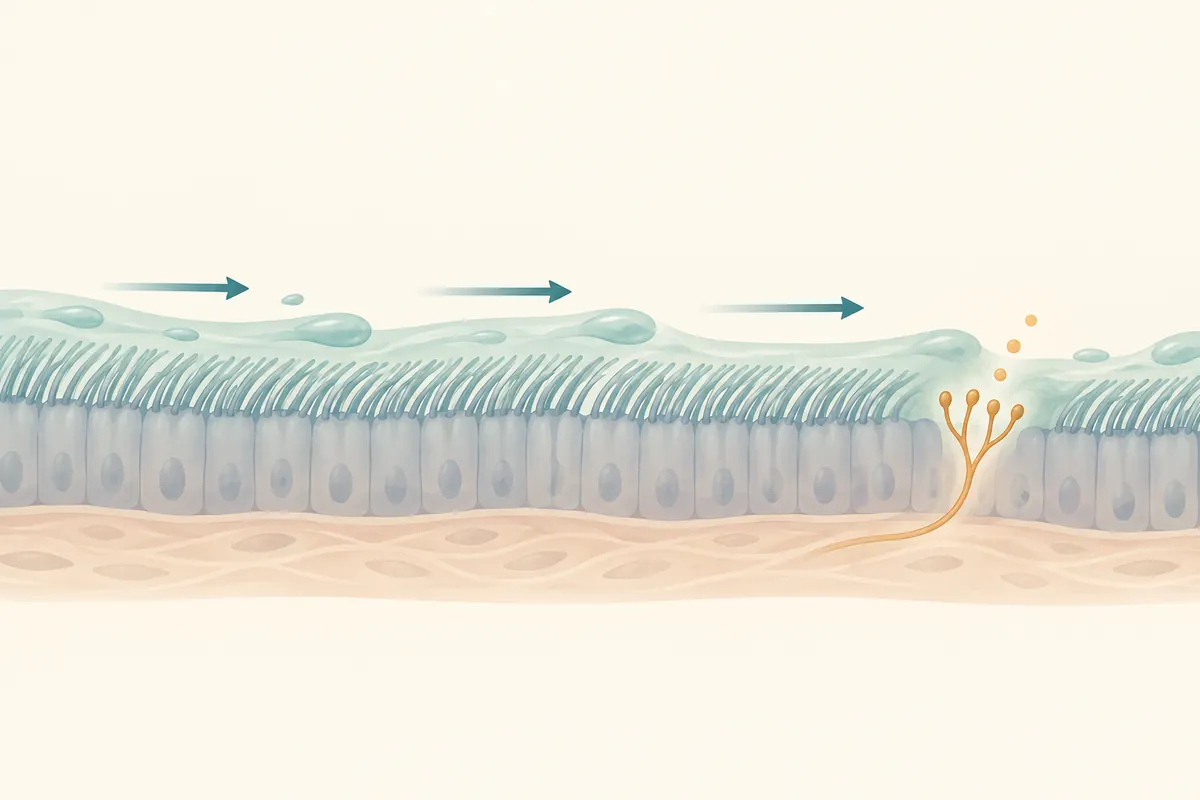
This schematic illustrates the location of the airway lining; it is not an image of an individual patient or evidence about what caused that person’s cough.
1. What is common in acute bronchitis?
The MSD Manual Professional Edition describes acute bronchitis as inflammation of the bronchial airways, commonly after an upper respiratory infection and usually caused by a virus. Cough is the main symptom; sputum may or may not be present. Sputum, including its color, does not by itself identify whether the cause is bacterial or viral.
The inner airway surface has tiny hair-like structures called cilia. The U.S. National Heart, Lung, and Blood Institute’s overview of primary ciliary dyskinesia explains that cilia move together in waves and carry mucus toward the mouth; mucus can contain inhaled dust and small particles. This basic anatomy helps locate the lining that becomes inflamed in bronchitis. It does not show that acute bronchitis damaged a particular person’s cilia or that ciliary function caused that person’s cough.
Cough may continue after other symptoms improve. The MSD review, updated in April 2025, says cough is often the last symptom to settle, commonly taking two to three weeks and sometimes longer. This is general information, not an individual diagnosis or forecast.
2. When the same symptoms may need a different assessment
A new cough in someone with asthma or chronic obstructive pulmonary disease may be assessed as a flare of the underlying condition rather than uncomplicated acute bronchitis. The MSD review also notes that clinicians consider whether symptoms such as breathlessness, chronic cough, or wheezing were present before the acute illness.
If you have difficulty breathing, high fever, or worsening symptoms, seek medical advice rather than assuming it is a routine episode of bronchitis. Whether pneumonia or another condition needs to be considered depends on examination findings and the person’s circumstances.
3. The scope of antibiotic guidance
The CDC guidance for adult outpatient care does not recommend routine antibiotics for uncomplicated acute bronchitis in adults, regardless of cough duration. Sputum color alone does not indicate bacterial infection. Assessment should consider whether findings suggest pneumonia.
This recommendation addresses uncomplicated acute bronchitis in adult outpatients in the United States. It should not be applied without qualification to children, severe illness, an exacerbation of an underlying condition, or a different diagnosis. CDC also notes that evidence for specific symptom-relief medicines is limited. Discuss personal treatment decisions with a clinician.
4. What this article can and cannot tell you
This article provides general information. It does not determine the condition of an individual’s airway cells or cilia, diagnose the cause of a cough, or establish whether antibiotics are needed. Sputum color and cough duration alone cannot answer those questions. Seek assessment if breathing becomes difficult, symptoms worsen, or high fever develops.
5. Sources
- Acute Bronchitis — MSD Manual Professional Edition (updated April 2025)
- Outpatient Clinical Care for Adults — CDC (updated April 16, 2024; U.S. adult outpatient guidance)